Journal of Cardiovascular Medicine and Cardiology
Description and Evolution of Alternative Access Route Options for Transcatheter Aortic Valve Implantation
Römstedter Straße 25, 29549 Bad Bevensen, Germany
Author and article information
Cite this as
Schäfer U, Burgdorf C. Description and Evolution of Alternative Access Route Options for Transcatheter Aortic Valve Implantation. J Cardiovasc Med Cardiol. 2026;13(5):81-83. Available from: 10.17352/2455-2976.000245
Copyright License
© 2026 Schäfer U, et al. This is an open-access article distributed under the terms of the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original author and source are credited.Abstract
Abbreviations
AKIN: Acute Kidney Injury Network; AS: Aortic Stenosis; LOS: Length of Stay; TA: Transapical; TAO: Transaortic/Direct Aortic; TAVI: Transcatheter Aortic Valve Implantation; TAX: Transaxillary; TC: Transcarotid; TCav: Transcaval; TF: Transfemoral; THV: Transcatheter Heart Valve; TAVR: Transcatheter Aortic Valve Replacement
Introduction
Over the last two decades, TAVI has emerged as a valuable treatment option (Class I, Level B) for patients with severe aortic stenosis (AS) who are at higher or moderate surgical risk for conventional aortic valve replacement with an age of ≥ 70 years [1]. Nowadays, the most frequently used access route is definitely the common femoral artery. But whenever the TF approach for TAVI or a surgical aortic valve replacement is not feasible, an alternative access route has to be considered (Class IIa LoE C) [1]. In recent years, the transapical (TA) approach has been largely displaced by other transvascular access routes, due to accumulating evidence that the TA approach is more likely associated with higher morbidity and mortality, when compared to transvascular access routes [2]. This observation is supported by a recent study comprising 129,821 patients of the national inpatient database (NID) of the United States (years 2011 to 2017), describing a rapid decline in TA utilization. After peaking in 2013 at 27.7%, the counts decreased to 1.92% in 2017, which was accompanied by higher inpatient mortality, increased length of stay, and higher costs in those patients with TA-TAVI [3]. Nevertheless, peripheral vascular disease is a common finding in patients who are candidates for TAVI [4]. For transvascular TAVI, sheath/introducer sizes range between 14F and 20F, depending on the valve size and the transcatheter heart valve (THV) delivery system. Thus, for most devices, a minimal vessel diameter of 5 to 6 mm is still required. In addition, in at least 10 to 15% of TAVI patients, a transfemoral (TF) approach seems not to be advisable due to significant peripheral artery disease or severe vessel tortuosity. Hence, the direct aortic (TAO), transcarotid (TC), transcaval (TCav), and transaxillary (TAX) implantation routes have been developed and applied to a broader extent over the last decade, but these alternative access routes are currently more frequently utilized in experienced high-volume centers [5-9].
Literature review
A focused literature search was conducted using PubMed to identify relevant publications addressing alternative access routes for transcatheter aortic valve implantation (TAVI). Publications from 2008 onward were considered. The search included the terms “TAVI,” “TAVR,” “transapical,” “direct aortic,” “transcaval,” “transcarotid,” and “transaxillary/transsubclavian.” Relevant publications addressing the use, outcomes, and evolution of alternative TAVI access routes were considered. Publications unrelated to alternative TAVI access were excluded.
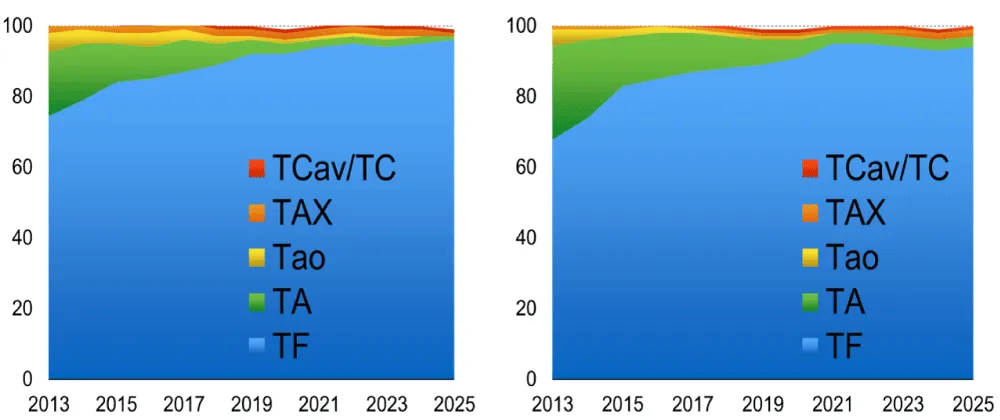
According to BiBa MedTech Research, the counts demonstrated a continuous rise between 2013 and 2025 for TF access utilization (in 2025: Europe 96%, Germany 94%; figure 1). Conversely, the largest decrease was found for the TA access route (in 2025: Europe 1%, Germany 3%) with similarly stable counts for the TAX access route (in 2025: Europe 2%, Germany 1%), TC/TCav access route (in 2025: Europe 1%, Germany 1%), whereas the TAO access route seems no longer to be utilized in Europe and Germany, respectively (Figure 1).
Until today, there is a great amount of variability in access utilization among various centers with regard to their first and second choice of access for TAVI. In some hospitals, the TAX approach is used in up to 20% of the cases [10]. Unfortunately, alternative TAVI approaches have not been studied comparatively, but available data suggest better outcomes for transvascular techniques compared to TA-TAVI (Table 1).
The studies summarized in Table 1 are heterogeneous with respect to study design, patient selection, sample size, study period, number of participating centers, endpoint definitions, and methods of outcome ascertainment. Therefore, the percentages presented should not be interpreted as directly comparable estimates of the relative safety or efficacy of the different access routes.
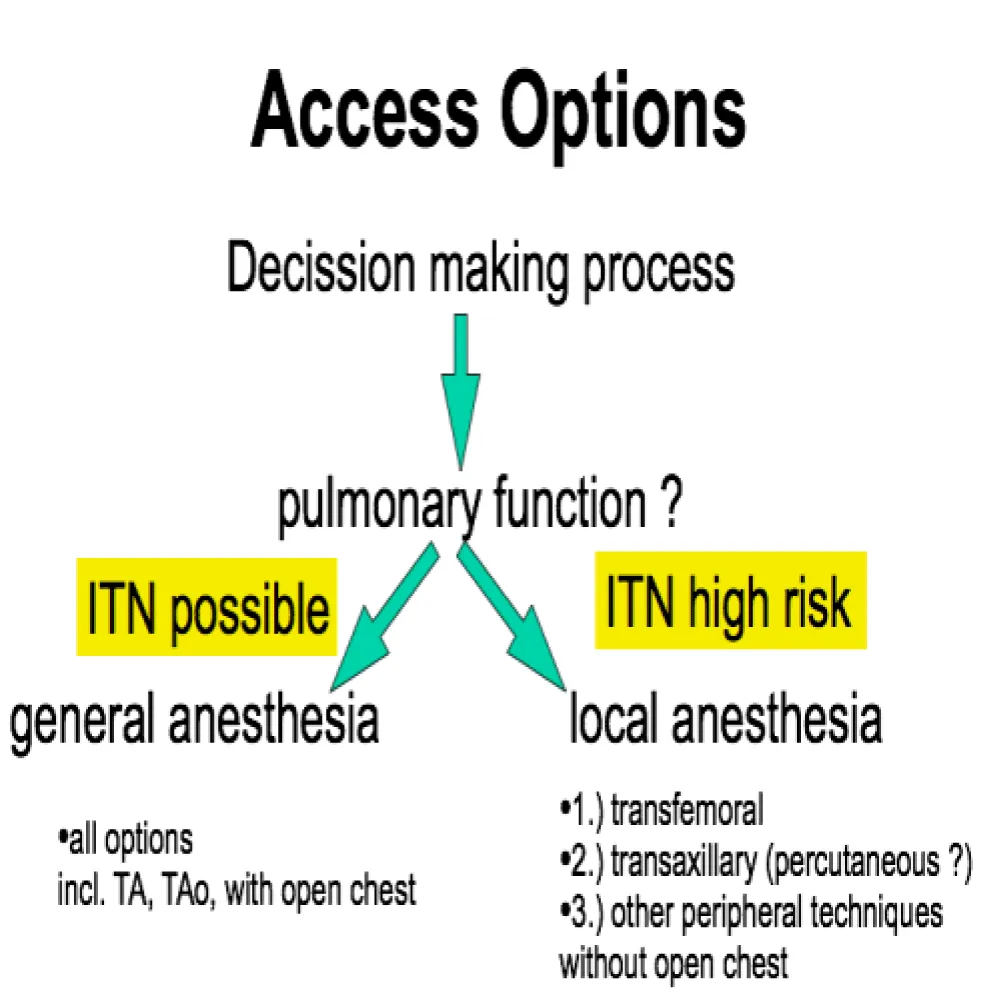
The various levels of invasiveness with corresponding outcomes vary between different access approaches and are derived from the available literature. But the choice of alternative access routes depends mainly on the experience and judgment of the heart team. Nevertheless, judgment of invasiveness varies among different investigators, albeit “central” access routes (e.g., TA and Tao) mandate intubation and ventilation, whereas other “peripheral” transvascular approaches allow for analgesia and/or local anesthesia only (Figure 2).
Moreover, practicability, ergonomics, and costs differ between various access approaches, which have been presented at several scientific meetings (Table 2).
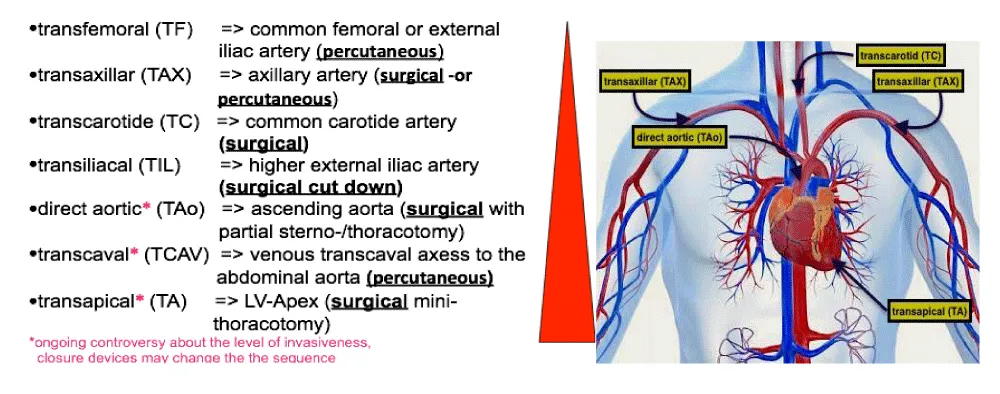
Last but not least, as previously mentioned, the various levels of invasiveness with corresponding outcomes significantly differ between the described access approaches and are derived from the available literature (Figure 3).
In summary, the frequencies of alternative access routes are significantly declining in recent years, but they still serve as an important supplement for those patients in whom the TF access route is not advisable. Each alternative access has advantages and disadvantages, so the access route should be tailored to the patients’ characteristics and needs. However, there is no standardized algorithm for choosing the optimal alternative vascular access. In addition, the TA access seems to be limited to a very select subset of patients with no other options. Possibly TA-TAVI will be eliminated in the near future, since the industry is no longer pursuing sales in a significantly declining market.
COI: U. Schäfer has received honoraria due to advisory board activities and grant support from Abbott Vascular, Medtronic Inc., New Valve Technology, Edwards Lifesciences, as well as honoraria from the speakers bureau of Edwards Lifesciences, Boston Scientific, New Valve Technology, Abbott Vascular, and Medtronic Inc.
References
- Praz F, Borger MA, Lanz J, Marin-Cuartas M, Abreu A, Adamo M, et al. 2025 ESC/EACTS Guidelines for the management of valvular heart disease: developed by the task force for the management of valvular heart disease of the European Society of Cardiology (ESC) and the European Association for Cardio-Thoracic Surgery (EACTS). Eur Heart J. 2025;46(44):4635-4736. Available from: https://doi.org/10.1093/eurheartj/ehaf194
- Vahanian A, Beyersdorf F, Praz F, Milojevic M, Baldus S, Bauersachs J, et al. 2021 ESC/EACTS Guidelines for the management of valvular heart disease. Eur Heart J. 2022;43(7):561-632. Available from: https://doi.org/10.1093/eurheartj/ehab395
- Sohal S, Mehta H, Kurpad K, Mathai SV, Tayal R, Visveswaran GK, et al. Declining trend of transapical access for transcatheter aortic valve replacement in patients with aortic stenosis. J Interv Cardiol. 2022:1-6. Available from: https://doi.org/10.1155/2022/5688026
- Smith CR, Leon MB, Mack MJ, Miller C, Moses JW, Svensson LG, et al. Transcatheter versus surgical aortic-valve replacement in high-risk patients. N Engl J Med. 2011;364:2187-2198. Available from: https://doi.org/10.1056/nejmoa1103510
- Lanz J, Greenbaum A, Pilgrim T, Tarantini G, Windecker S. Current state of alternative access for transcatheter aortic valve implantation. EuroIntervention. 2018;14:AB40-AB52. Available from: https://doi.org/10.4244/eij-d-18-00552
- Eng MH, Qintar M, Apostolou D, O'Neill WW. Alternative access for transcatheter aortic valve replacement: a comprehensive review. Interv Cardiol Clin. 2021;10(4):505-517. Available from: https://doi.org/10.1016/j.iccl.2021.06.001
- Morello A, Corcione N, Ferraro P, Cimmino M, Pepe M, Cassese M, et al. The best way to transcatheter aortic valve implantation: from standard to new approaches. Int J Cardiol. 2021;322:86-94. Available from: https://doi.org/10.1016/j.ijcard.2020.08.036
- Banks A, Gaca J, Kiefer T. Review of alternative access in transcatheter aortic valve replacement. Cardiovasc Diagn Ther. 2020;10(1):72-82. Available from: https://doi.org/10.21037/cdt.2019.10.01
- Young MN, Singh V, Sakhuja R. A review of alternative access for transcatheter aortic valve replacement. Curr Treat Options Cardiovasc Med. 2018;20(7):62. Available from: https://doi.org/10.1007/s11936-018-0648-5
- Petronio AS, De Carlo M, Bedogni F, Maisano F, Ettori F, Klugmann S, et al. 2-year results of CoreValve implantation through the subclavian access: a propensity-matched comparison with the femoral access. J Am Coll Cardiol. 2012;60:502-507. Available from: https://doi.org/10.1016/j.jacc.2012.04.014
- Schäfer U, Ho Y, Frerker C, Schewel D, Sanchez-Quintana D, Schofer J, et al. Direct percutaneous access technique for transaxillary transcatheter aortic valve implantation: "the Hamburg Sankt Georg approach." JACC Cardiovasc Interv. 2012;5:477-486. Available from: https://doi.org/10.1016/j.jcin.2011.11.014
- Schäfer U, Deuschl F, Schofer N, Frerker C, Schmidt T, Kuck KH, et al. Safety and efficacy of the percutaneous transaxillary access for transcatheter aortic valve implantation using various transcatheter heart valves in 100 consecutive patients. Int J Cardiol. 2017;232:247-254. Available from: https://doi.org/10.1016/j.ijcard.2017.01.010
- Mylotte D, Sudre A, Teiger E, Obadia JF, Lee M, Spence M, et al. Transcarotid transcatheter aortic valve replacement: feasibility and safety. JACC Cardiovasc Interv. 2016;9(5):472-480. Available from: https://doi.org/10.1016/j.jcin.2015.11.045
- Greenbaum AB, Babaliaros VC, Chen MY, Stine AM, Rogers T, O'Neill WW, et al. Transcatheter access and closure for transcatheter aortic valve replacement: a prospective investigation. J Am Coll Cardiol. 2017;69(5):511-521. Available from: https://doi.org/10.1016/j.jacc.2016.10.024
- Greenbaum AB, O'Neill WW, Paone G, Guerrero ME, Wyman JF, Cooper RL, et al. Caval-aortic access to allow transcatheter aortic valve replacement in otherwise ineligible patients: initial human experience. J Am Coll Cardiol. 2014;63(25 Pt A):2795-2804. Available from: https://doi.org/10.1016/j.jacc.2014.04.015
- Bapat V, Frank D, Cocchieri R, Jagielak D, Bonaros N, Aiello M, et al. Transcatheter aortic valve replacement using transaortic access: experience from the multicenter, multinational, prospective ROUTE registry. JACC Cardiovasc Interv. 2016;9(17):1815-1822. Available from: https://doi.org/10.1016/j.jcin.2016.06.031
- Thourani VH, Jensen HA, Babaliaros V, Suri R, Vemulapalli S, Dai D, et al. Transapical and transaortic transcatheter aortic valve replacement in the United States. Ann Thorac Surg. 2015;100(5):1718-1726. Available from: https://doi.org/10.1016/j.athoracsur.2015.05.010
Advertisement



 Save to Mendeley


